



ABSTRACT:
OBJECTIVE: Depression is a common and debilitating disorder affecting millions of people. First-line
treatments fail to achieve remission in approximately one-third of patients, highlighting
a critical need for treatment. Transcranial direct current stimulation (tDCS) has
emerged as a novel treatment for depression. Therefore, the aim of this review was
to provide a comprehensive overview of the last decade of tDCS trials for depression
and to suggest future research directions.
METHODS: To synthesize studies from the past decade, we conducted a systematic review and meta-analysis
of randomized clinical trials (RCTs) of tDCS for depression.
RESULTS: A total of 21 RCTs were included, showing a moderate effect of active tDCS compared
to placebo. We also provided a description of study designs, stimulation parameters,
and patient characteristics. We then proposed possible strategies to improve clinical
efficacy and reduce outcome variability, including 1) optimization/personalization
of tDCS through spatial and temporal target localization, 2) optimized methodological
strategies, including home-based, accelerated tDCS protocols and novel study designs,
and 3) investigation of the patient profile to identify characteristics that may predict
treatment response.
CONCLUSION: tDCS shows promise as a treatment for depression, but variability in study parameters
and outcomes underscores the need for further optimization. Refinement and standardization
of protocols may improve its efficacy.
Keywords: Depression; transcranial direct current stimulation; randomized clinical trials; review.
FIGURES
| Note: How to cite this article: da Silva PHR, Vanderhasselt MA, Pilloni G, Charvet L, Padberg F, Bikson M, et al. Challenges and future directions of transcranial direct current stimulation for depression: insights from a systematic review and meta-analysis. Braz J Psychiatry. 2025;47:e20243989. http://doi.org/10.47626/1516-4446-2024-3989 |
| Received: October 25 2024; Accepted: January 8 2025 |
INTRODUCTION
Depression is a prevalent and debilitating mental health disorder that affects millions worldwide, significantly impairing daily functioning, work productivity, and overall quality of life.1 First-line treatments typically include pharmacotherapy and psychotherapy. While these conventional therapies benefit many patients, a substantial subset does not respond adequately, experiencing persistent symptoms, adverse effects, and generating a significant economic burden on society.1,2 With nearly one-third of patients failing to achieve remission despite multiple interventions, identifying effective alternative treatments is crucial.
Over the past two decades, extensive research has advanced the clinical use of noninvasive brain stimulation (NIBS) techniques, particularly as promising treatments for depression.3 Repetitive transcranial magnetic stimulation (rTMS) and electroconvulsive therapy (ECT) have been shown to be effective in alleviating depressive symptoms. However, both require specialized equipment and clinical settings, limiting patient accessibility.4 In contrast, transcranial direct current stimulation (tDCS) presents a more accessible alternative. This intervention involves applying a low electrical current to the scalp to modulate neuronal excitability and plasticity.5,6 Compared to first-line treatments and other NIBS approaches, tDCS has a favorable safety profile with minimal side effects.7 Additionally, its potential for home-based application can improve accessibility for patients with mobility limitations or those in remote areas.8,9
In 2000, Nitsche & Paulus10 published a seminal study demonstrating that applying anodal tDCS over the motor cortex at 1 mA increased cortical excitability, while cathodal stimulation decreased it after a 5-minute session. Subsequent studies explored the mechanisms of action and neurophysiological effects of tDCS on the motor cortex by assessing its modulation following pharmacological interventions. These studies showed that tDCS could induce long-lasting effects, likely due to enhanced N-methyl-D-aspartate (NMDA) receptor efficacy with anodal stimulation and reduced efficacy with cathodal stimulation.11
Such findings, along with advances in the understanding of depression - such as neuroimaging studies identifying markers of frontal lobe dysfunction, characterized by hypoactivity in the left hemisphere and hyperactivity in the right12 - led to the first pilot study investigating tDCS as a treatment for depression. Fregni et al.13 examined the effects of five days of 20-minute anodal stimulation of the left dorsolateral prefrontal cortex (DLPFC) at 1 mA (with the cathode placed over the right DLPFC and the anode over the left) in patients with major depression. The study found that active tDCS significantly improved depressive symptoms compared to sham stimulation. Further pilot studies corroborated the efficacy of tDCS in the treatment of depressive symptoms.14-16
However, more recent clinical trials and meta-analyses have reported mixed findings on the efficacy of tDCS as a treatment for depression,17,18 possibly due to high variability in tDCS parameters across studies. Additionally, ongoing neurophysiological research has shown that the mechanisms of action of tDCS are complex and non-linear, particularly in the prefrontal cortex (PFC).19,20 These factors suggest further optimization of tDCS protocols is necessary to enhance its effectiveness in treating depression.
This review aimed to quantitatively assess the efficacy of tDCS for depression over the past decade while providing a comprehensive overview of clinical findings and methodological variability across studies and patient samples. Additionally, we discuss future directions for the field, highlighting strategies to optimize treatment protocols, enhance methodological rigor, and advance scientific understanding.
METHODS
Search strategy and eligibility criteria
This meta-analysis was conducted following the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) guidelines.21 To evaluate the characteristics of tDCS randomized clinical trials (RCTs) for depression over the past decade, we performed a systematic search in the PubMed database (January 1, 2014, to July 1, 2024), focusing on RCTs published within this period. The search was conducted using key terms such as "tDCS," "depression," and "RCT." We included full-text, English-language studies that were randomized, placebo-controlled trials investigating the effects of active tDCS versus sham tDCS in adult participants experiencing an acute depressive episode.
Data extraction
From the identified studies, we extracted several variables such as year of publication, sample size, mean depression scale scores of both active and sham groups from baseline and endpoint (although only endpoint scores were used for analysis), type of depression diagnosis, inclusion of treatment resistant-depression (TRD) patients, number of tDCS sessions, duration of treatment, tDCS electrode positioning, size and format, and tDCS current density and intensity.
Assessment of risk of bias
Risk of bias was evaluated using the Cochrane Risk of Bias Tool.22 The assessment included the following domains: allocation, blinding of participants, handling of missing data, blinding of outcome assessment, and selective reporting. Each domain was classified as having a low, unclear/some concerns, or high risk of bias.
Statistical analysis
A meta-analysis was conducted on the included studies using R Statistical Software (v4.2.2; R Core Team, 2022). Sample size, SD, and mean endpoint scores from both active and sham groups were used to calculate effect sizes. A random effects model was applied, with Hedges' g as the effect size measure. For the meta-analytic approach, the "metafor" package23 was used to synthesize data and evaluate the overall effect of tDCS (vs. sham tDCS) on depressive symptoms. Additionally, a series of meta-regressions and subgroup analyses were conducted based on available methodological and clinical variables.
RESULTS
Our search identified 21 RCTs investigating the efficacy of tDCS for treating depression17,18,24-42 (Supplementary Figure S1). Overall study characteristics are summarized in Table 1. The meta-analysis included 1,367 participants, with a mean age of 41.6 years, of whom 61.5% were women.
| Clinical and depression characteristics | tDCS parameters | Study design | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Author | Sample size (active and sham) | Women (%) | Mean age | Treatment resistant | Diagnosis | Curren tintensity (mA) | Electrodesize (cm2) | Number of sessions | Anodeposition | Cathodeposition | Sessionduration (min) | Arms |
| Aust40 | 95 | 53.0 | 40.9 | No | MDD | 2 | 35 | 12 | F3 | F4 | 30 | 2 arms: CBT + active tDCS/CBT + sham tDCS |
| Bennabi44 | 47 | 64.4 | 60.2 | Yes | MDD | 2 | 35 | 10 | F3 | Fp2 | 30 | 2 arms: ative tDCS/sham tDCS in nonresponders to escitalopram |
| Borrione17 | 146 | 86.3 | 39.0 | Yes | MDD | 2 | 22.9 | 21 | F3 | F4 | 30 | 3 arms home-based: active tDCS + iBT/active tDCS + placebo iBT/placeo tDCS + placebo iBT |
| Brunoni24 | 37 | 29.0 | 43.8 | Yes | MDD | 2 | 25 | 10 | F3 | F4 | 30 | 2 arms: active tDCS + cognitive training/placebo tDCS + cognitive training |
| Brunoni26 | 154 | 68.0 | 42.8 | Yes | MDD | 2 | 25 | 22 | F3 | F4 | 30 | 3 arms (non-inferiority trial): active tDCS/escitalopram/placebo |
| Burkhardt18 | 160 | 59.0 | 40.1 | Yes | MDD | 2 | 35 | 24 | F3 | F4 | 30 | 2 arms: ative tDCS/sham tDCS in non-responders to SSRIs |
| Lee37 | 64 | 73.4 | 33.4 | Yes | Bipolar | 2 | 28.26 | up to 42 | F3 | F4 | 30 | 2 arms home-based: active tDCS/sham tDCS |
| Loo27 | 84 | 50.0 | 48.1 | Yes | MDD/bipolar | 2.5 | 35 | 20 | F3 | F8 | 30 | 2 arms: active tDCS/sham tDCS |
| Mayur28 | 16 | 37.5 | 45.0 | Yes | MDD | 2 | 25 | 10 | F3 | F4 | 30 | 2 arms: active tDCS + ECT/sham tDCS + ECT |
| Moirand29 | 39 | 61.5 | 49.8 | Yes | MDD | 2 | 35 | 10 | F3 | F4 | 30 | 2 arms: active tDCS/sham tDCS |
| Nord30 | 39 | 51.3 | 33.3 | Yes | MDD | 1 | 35 | 8 | F3 | Deltoid | 20 | 2 arms: CBT + active tDCS/CBT + sham tDCS |
| Pavlova31 | 69 | 72.0 | 38.3 | No | MDD | 0.5 | 26.2 | 10 | F3 | Fp2 | 25 | 3 arms: active 30 min tDCS/active 20 min tDCS/sham tDCS |
| Sampaio-Junior39 | 59 | 68.0 | 45.9 | No | Bipolar | 2 | 25 | 12 | F3 | F4 | 30 | 2 arms: active tDCS/sham tDCS |
| Salehinejad32 | 30 | 56.6 | 28.3 | N/I | MDD | 2 | 35 | 10 | F3 | F4 | 20 | 2 arms: active tDCS/sham tDCS |
| Salehinejad33 | 24 | 62.5 | 26.2 | N/I | MDD | 2 | 35 | 10 | F3 | F4 | 20 | 2 arms: active tDCS/sham tDCS |
| Segrave34 | 18 | 37.0 | 41.6 | N/I | MDD | 2 | 35 | 5 | F3 | F8 | 24 | 3 arms: active tDCS + CCT/sham tDCS + CCT/sham CCT + active tDCS |
| Sharafi35 | 30 | 53.0 | 47.3 | Yes | MDD | 2 | 20 | 10 | F3 | F4 | 20 | 2 arms: active tDCS/sham tDCS |
| Valiengo38 | 48 | 50.0 | 61.6 | No | Post-stroke | 2 | 25 | 12 | F3 | F4 | 30 | 2 arms: active tDCS/sham tDCS |
| Vigod41 | 20 | 100.0 | 32.3 | No | Post-partum | 2 | 35 | 15 | F3 | F4 | 30 | 2 arms: active tDCS/sham tDCS |
| Welch36 | 14 | 85.7 | 54.8 | Yes | MDD | 2 | 25 | 12 | F3 | F4 | 30 | 2 arms: active tDCS + eCBT/sham tDCS + eCBT |
| Woodham42 | 174 | 69.0 | 37.7 | No | MDD | 2 | 23 | 36 | F3 | F4 | 30 | 2 arms home-based: active tDCS/sham tDCS |
CBT = cognitive behavioral therapy; CCT = cognitive control task; eCBT = online cognitive behavioral therapy; ECT = electroconvulsive therapy; iBT = internet-based therapy; mA = milliamperes; MDD = major depressive disorder; N/I = not informed; SSRI = selective serotonin reuptake inhibitor.

The meta-analysis demonstrated a moderate overall effect size for active tDCS compared to placebo (Hedges' d = 0.40; 95%CI 0.18-0.60) (Supplementary Figure S2). These findings align with previous research in the field,43,44 further supporting the therapeutic potential of tDCS for treating depression.
Meta-regressions and subgroup analyses were performed using various clinical and methodological variables, including cathode position, electrode size, current density, number of sessions, total treatment duration (in weeks), protocol combinations, use of home-based interventions, diagnosis, and TRD severity. However, none of these variables showed a significant effect compared to sham tDCS (Supplementary Material S3).
Study characteristics
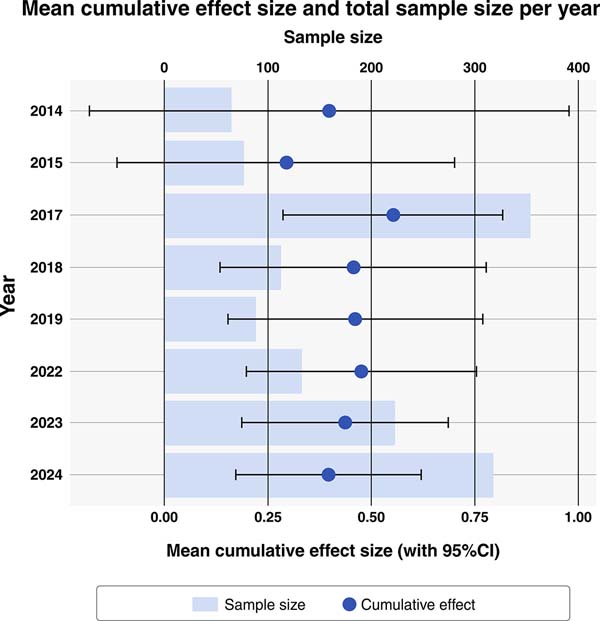
The assessment of risk of bias revealed 61.9% of studies were rated as having low risk, 9.5% raised some concerns, and 28.6% were deemed high risk. A more detailed evaluation of the risk of bias is provided in Supplementary Table S1. An important trend observed across study designs in recent years is the increase in sample size. Between 2014 and 2018, the average sample size was 50.8 participants per trial, while in the past five years, there has been a substantial increase, with a mean sample size of 85.3 participants (Figure 1). This growth reflects positive advancements in methodological approaches within the field. Additionally, over the past two years, tDCS trials have started to assess the feasibility, safety, and tolerability of home-based tDCS treatments,17,37,42 offering an excellent opportunity to increase the number of sessions and extend the treatment duration.
Patient characteristics
Over the past decade, studies have included patients with major depressive disorder (MDD) - both with and without TRD - as well as individuals with bipolar, poststroke, and postpartum depression. Most studies (17 RCTs) included patients with TRD, defined as those who had not responded to prior treatment modalities. The degree of treatment resistance varied, ranging from individuals who had failed a single pharmacotherapy to those unresponsive to multiple treatment trials over extended periods. Previous meta-analyses have suggested individuals with TRD tend to respond less favorably to tDCS compared to those with less severe depression, potentially contributing to a reduced overall treatment effect.44 However, our meta-regression analysis did not identify TRD as a significant factor influencing the overall effects of tDCS. This discrepancy may be explained by differences in data granularity. The previous meta-analysis that identified TRD as a significant moderator was based on individual-level data, whereas our analysis relies on study-level aggregates, which are less sensitive to variability in patient characteristics.
Most studies included patients who were already on a stable but ineffective antidepressant regimen. Only four studies examined tDCS as a standalone therapy, without the use of additional medications. The concomitant use of medication introduces a complex dynamic when combined with tDCS.45 For example, some antidepressants may enhance the effects of tDCS by facilitating neuroplasticity, whereas other medications, such as benzodiazepines, may reduce neural excitability, potentially diminishing tDCS efficacy.46
In contrast to the extensive research on tDCS for MDD, studies examining its application for secondary depression and bipolar depression remain relatively limited. Only two studies have investigated tDCS for secondary depression, specifically poststroke and postpartum depression,38,41 both of which reported positive outcomes. Similarly, only three studies have explored the potential benefits of tDCS for bipolar depression. While one study demonstrated significant effects,39 subsequent research failed to replicate these findings.27,37 These inconsistencies highlight the need for further research to clarify the role of tDCS in treating secondary depression and bipolar depression.47
Stimulation parameters
Electrode positioning
Electrodes are typically placed using a standard bifrontal configuration, with minimal variation since the earliest studies. However, methods for determining electrode placement vary significantly across RCTs, and specific details on how target locations are identified are often underreported. Most studies rely on the EEG 10-20 system to label electrode placement sites. In the studies included in this review, the anode was predominantly positioned at F3, which roughly corresponds to the DLPFC, in 20 out of 21 studies. One study used the OLE montage, where the anode is positioned closer to F5.48 Cathode placement varied slightly around the nominal F4 position (n=15 studies) and included F6 (n=1), Fp2 (n=2), and F8 (n=2), all of which correspond to the right DLPFC. However, one trial deviated from this pattern by placing the cathode over the deltoid muscle.30,49
Current intensity and density
Current intensity has remained relatively consistent over the years, with only three studies deviating from the standard 2 mA. Notably, only one study employed a higher intensity of 2.5 mA, exceeding the typical 2 mA used in most tDCS trials. Interestingly, this study found no significant differences between the active and sham groups, with the sham group showing numerically greater improvement. This unexpected result suggests that higher current intensities may not necessarily enhance therapeutic benefits.27
Electrode size varies across studies, leading to inconsistencies in current density (the ratio of electric current intensity to electrode area) across trials. Regarding electrode dimensions: 10 studies used 35 cm2 rectangular electrodes; six trials used 25 cm2 square electrodes; one study used 20 cm2 square electrodes; one study used electrodes of different sizes (3.5 × 5 cm and 5 × 7 cm); three recent RCTs have shifted to round electrodes (22.9 cm2, 28.26 cm2, and 23 cm2).37,39,42 This transition from rectangular and square electrodes to round electrodes in recent studies highlights the evolving methodology in tDCS research. Even subtle deviations in tDCS dosing parameters, such as electrode positioning, can influence outcomes. Therefore, when reviewing tDCS trials for depression and considering future applications, it is essential not to conflate distinct tDCS doses.50
Session duration
The duration of stimulation sessions has remained relatively consistent throughout tDCS trials for depression. Most RCTs (15 out of 21 studies) employed 30-minute sessions, while the remaining trials used slightly shorter durations, ranging from 20 to 25 minutes.30-35
Number of sessions and weeks
The number of tDCS sessions varied widely across studies, ranging from 5 to 42 sessions. The shortest protocol consisted of five consecutive sessions administered over a single workweek,34 whereas the most extensive treatment applied 42 sessions, with one session per day.37 Another long-term study implemented a 36-session protocol, starting with daily sessions for three weeks, followed by a reduced frequency of three sessions per week, extending the treatment duration to 10 weeks.42 Other studies with similarly extensive regimens applied 21, 22, and 24 sessions. These trials generally began with an intensive phase lasting 3 to 4 weeks, during which sessions were conducted daily, followed by a gradual reduction in frequency to once or twice per week.
Two other trials followed the same strategy but with fewer sessions, implementing an acute phase of 10 sessions, followed by two additional sessions in a later week, totaling 12 sessions. Another two trials applied only an acute treatment phase, without tapering, delivering 15 and 20 sessions, respectively. Two studies adopted an accelerated protocol, administering two sessions per day over 5 days, for a total of 10 sessions.25,29 Additionally, seven studies applied a similar 10-session protocol, but spread over 2 weeks. Finally, two trials combined tDCS with cognitive behavioral therapy (CBT). One study provided eight sessions over 8 weeks,30 while the other delivered 12 sessions over 6 weeks, with two sessions per week.40
Interestingly, despite the variability in the number of tDCS sessions across trials, recent meta-analyses suggest the total number of sessions may not be a significant factor in determining the overall effectiveness of tDCS for treating depression.43,44 However, a recent study examining the time course of tDCS response in depression found the duration of the treatment period may play a crucial role in its effectiveness. Specifically, studies that extend treatment over a longer period tend to yield better results since the placebo response gradually diminishes over time.51
Combined protocols
Nine of the 21 studies explored whether combining tDCS with other depression treatments could enhance therapeutic outcomes. These studies integrated tDCS with various interventions, including CBT, antidepressants, cognitive training, and ECT. Initial findings were promising, particularly in studies where tDCS was combined with cognitive training,34 cognitive therapy,24,34,36 or medication,15,31 all of which demonstrated enhanced antidepressant effects. However, later research that combined tDCS with CBT, ECT, and internet-based therapy did not show a significant increase in therapeutic effects when active tDCS was used alongside these interventions.17,28,30,40 Interestingly, the variability in protocols across studies may have contributed to these inconsistent results, as the interventions targeted distinct neurobiological mechanisms. Additionally, the timing of combined therapies could play a crucial role in determining their effectiveness.46
Sham protocols
Over the past decade, sham tDCS protocols for depression have been implemented using three main approaches. The most common method, used in nine RCTs, involved delivering a brief period of active current at the beginning of the session, including a ramp-up, a short continuous current, and a ramp-down.24,28,29,31-33,35,38,41 This approach aims to replicate the initial sensations of real stimulation without sustaining the current throughout the session. A second approach, used in five studies, applied a gradual ramp-up and ramp-down without any continuous stimulation in between. This method mimics the sensation of tDCS without delivering actual current.17,27,30,40,42,52 Finally, six RCTs employed a sham protocol featuring a double ramp-up/down procedure, both at the beginning and end of the session. This design further enhances the simulation of active stimulation while maintaining the placebo nature of the intervention. One study did not provide details on its sham protocol methodology.25
There is still no consensus on the optimal sham protocol for tDCS in the treatment of depression. However, Loo et al.27 suggested a steady current of 0.034 mA used in their sham protocol may have produced modulatory effects, potentially influencing study outcomes. Additionally, recent literature indicates that sham protocols employing a short continuous current or a single ramp-up/down at the beginning of the session may be more effective in eliciting a placebo response. This could be due to their superior ability to maintain blinding.53
DISCUSSION
The future of transcranial direct current stimulation for depression: a 5-year perspective
Over the past decade, 21 RCTs have investigated the effects of tDCS on depression, with a primary focus on MDD in individuals who have not responded to previous treatments. Most studies have applied a relatively uniform current intensity, with electrodes placed over the DLPFC, predominantly in a bilateral configuration. Notably, methodological quality has significantly improved in recent years, largely due to larger sample sizes in more recent trials. However, methodological heterogeneity remains high, likely due to the lack of consensus on optimal tDCS protocols for depression.
Optimized and personalized approaches have significant potential to enhance efficacy, reduce individual variability, and ultimately improve the therapeutic effects of tDCS.54 Refining these strategies could also strengthen the case for regulatory bodies to consider tDCS as a recommended treatment for depression. Methodological adjustments such as refining target locations and electrode montage through electric field (EF) distribution55,56 or network-based approaches,57,58 identifying patient-specific profiles, and optimizing stimulation protocols are key strategies that could improve tDCS efficacy in depression. Such aspects are explored in the following section.
Spatial optimization
A key objective in target optimization is to ensure that the desired brain region receives the maximum EF intensity across individuals. Recent studies investigating EF density have shown that the induced fields vary significantly among individuals, even when the same tDCS montage and current intensity are used. This variability arises from current dispersion through multiple tissue layers, including skin, bone, and brain tissue.59 Anatomical differences among individuals can therefore alter the distribution and intensity of the current reaching targeted brain regions, as demonstrated in previous research.60
To account for this variability, personalizing the tDCS dose for each individual may be crucial. For example, a secondary analysis of data from the Electric Current Therapy for Treating Depression Clinical Study (ELECT-TDCS) trial26 found that EF intensity differs across individuals and that higher EF magnitudes in regions such as the anterior cingulate cortex (ACC) and the DLPFC were positively associated with greater improvement in depressive symptoms.61 Such findings reinforce the idea that individual differences in EF distribution can influence tDCS effectiveness as a treatment for depression.
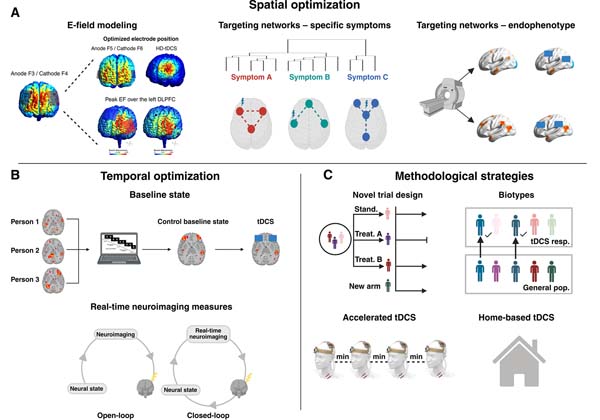
Modeling studies have revealed that bilateral DLPFC tDCS, the most common montage for depression, often generates EF peaks in the medial frontopolar area,62 rather than in the intended target region. Therefore, achieving the optimal montage requires careful consideration not only of electrode placement but also orientation and size, ensuring that the peak EF current is centered over the targeted brain area (Figure 2A). The bilateral montage is not fully standardized across studies. Various craniometric procedures have been used in recent years, including headband setups such as the OLE montage26 and home-based standardized montages.37,42 Additionally, most studies do not report the precise methodology for target localization, which introduces further variability in EF distribution. To improve accuracy, EF simulations can be performed before selecting an electrode montage using software such as SimNIBS63 and ROAST.64 These tools, which utilize generic head models,65,66 help determine optimal electrode placement, size, and orientation, factors often overlooked in tDCS studies67 (Figure 2A). However, the use of individualized magnetic resonance imaging (MRI) scans is recommended, as they offer a more precise targeting.68

New approaches to address spatial variability
Unlike the traditional two-electrode approach, high-definition tDCS (HD-tDCS) (Figure 2A) utilizes an array of smaller electrodes arranged in specific configurations. This technique is designed to provide more precise targeting of brain regions and enables the delivery of electric current to deeper cortical areas.69 Interestingly, a recent sham-controlled clinical trial investigating HD-tDCS demonstrated only active HD-tDCS - and not traditional tDCS - engaged the targeted brain region. Additionally, active HD-tDCS induced significantly stronger changes in cerebral blood flow70 and also gray matter.71
Functional targeting, which involves identifying specific brain regions or networks that are functionally relevant to an individual's symptoms (Figure 2A), represents another promising approach for enhancing clinical outcomes. Since brain regions engage and respond to tDCS as part of interconnected networks.72,73 This is particularly relevant for depression, which is increasingly recognized as a network disorder.74 For example, a study in healthy individuals demonstrated that tDCS applied over the left DLPFC can enhance connectivity between the DLPFC and other brain regions involved in mood regulation.75 Focusing on specific networks related to MDD, tDCS could be used to explore how modulating these networks might help alleviate specific depressive symptoms.76
Temporal optimization
The timing of concomitant interventions, whether performed before, during, or after a tDCS session, can significantly influence clinical outcomes.77 For example, pre-conditioning the brain with cognitive tasks may enhance tDCS efficacy. Recent research78 suggests stronger effects were observed in healthy individuals when tDCS was paired with a more difficult version of a cognitive control training task, compared to an easier version. However, sham-controlled trials combining tDCS with psychological interventions have not demonstrated significant antidepressant improvements in recent depression studies.17,30,40 This may be due to the complex nature of psychotherapy, which involves the activation of diffuse neural networks and requires multiple cognitive and emotional processes.79 In these trials, the simultaneous application of tDCS and psychotherapy may have diluted the effects of each intervention due to competing demands on cognitive resources or suboptimal engagement of the targeted neural circuits.80 To achieve more robust and linear effects, tDCS may be better suited for combination with mechanistically defined interventions, such as cognitive training, cognitive tasks, or bodily interventions (Figure 2B). These approaches are more likely to activate specific cognitive domains.46,81
Moreover, given the variability of individual brain states and the heterogeneity of depression, optimizing the timing and sequencing of cognitive interventions and tDCS may require tailoring treatments to the unique neural and psychological profile of each patient. This approach could incorporate real-time neuroimaging measures, such as open- and closed-loop EEG, to identify the most effective brain state for stimulation. By ensuring tDCS is delivered when the brain is most receptive, treatment efficacy may be enhanced (Figure 2B). When combined with concurrent brain imaging, these stimulation techniques can also provide insights into neuronal activity patterns during shifting brain states, allowing for closed-loop systems.77
Optimized methodological strategies
Home-based transcranial direct current stimulation
One of the primary advantages of home-based tDCS is its accessibility and convenience. By allowing patients to self-administer treatment at home, this approach eliminates the need for frequent clinic or hospital visits. As a result, a much broader population can access tDCS therapy, including individuals facing barriers related to time, cost, or location. Additionally, home-based tDCS has the potential to be more cost-effective, reducing healthcare expenses for both patients and providers. This affordability makes it an appealing alternative for individuals who may not have access to traditional therapies due to financial or logistical constraints (Figure 2C).
In recent years, advancements in tDCS technology have made home-based application increasingly feasible.8 Modern user-friendly devices are designed for safe and effective use in non-clinical settings, expanding accessibility to a broader population. Currently, most home-based tDCS studies for depression consist of pilot projects, case reports, and open-label trials with small sample sizes.37,82-90 To date, three RCTs investigated home-based tDCS for depression, all reporting good safety and feasibility outcomes.17,37,42 However, two of these trials did not find significant benefits of home-based tDCS compared to sham treatment.17 A possible explanation for these mixed results is the lack of professional oversight, which may lead to improper use of the tDCS device and variability in treatment parameters (commentary in Borrione et al.17). Such challenges raise concerns about both efficacy and safety when tDCS is administered without expert guidance. Addressing these issues is crucial not only for establishing tDCS as a viable home-based treatment but also for expanding its applications in other key areas.
Home-based tDCS could play a significant role in the long-term management of depression, enabling patients to sustain therapeutic benefits over extended periods from the comfort of their homes.91 In this context, tDCS could serve as an effective follow-up treatment to other interventions, such as rTMS, by helping to reinforce and prolong its effects. Unlike current rTMS treatments, home-based tDCS could eliminate the need for frequent visits to research and clinical centers.
Accelerated transcranial direct current stimulation
Accelerated tDCS involves administering more than one therapeutic session per day, with the goal of achieving faster and potentially more robust clinical outcomes. Two RCTs have investigated this approach in MDD patients, delivering 10 sessions over 5 days. While one study found no significant differences between active and sham tDCS,25 the other reported a higher remission rate in the active group.29 Additionally, a third RCT examining accelerated tDCS for vascular depression demonstrated greater efficacy in reducing symptoms compared to standard daily tDCS and sham.92
Expanding on this concept, a recent open-label trial explored an even more intensive protocol, in which participants underwent five tDCS sessions per day over 10 days, totaling 50 sessions.93 The results suggested this intensive approach was safe, well-tolerated, and feasible, with preliminary evidence of positive clinical effects. However, the lack of a placebo group - a crucial consideration given the high placebo response rates in depression treatments - highlights the need for placebo-controlled trials to accurately assess the true efficacy of accelerated tDCS (Figure 2C).
Innovate trial designs
Traditional RCTs typically test fixed tDCS protocols under rigid conditions, which may overlook important individual variations in treatment response. In contrast, more adaptive clinical trial designs, such as platform trials and response-adaptive trials, offer greater flexibility and efficiency in evaluating multiple treatment parameters94 (Figure 2C). Platform trials enable the simultaneous comparison of different tDCS protocols - including variations in electrode placement, current intensity, and session duration - within a single trial. This approach allows researchers to rapidly discard ineffective interventions while identifying promising treatment strategies, accelerating the refinement of tDCS protocols. Response-adaptive trials take this further by dynamically adjusting treatment allocation based on real-time patient responses. In these designs, individuals who respond favorably to certain tDCS settings may receive those protocols more frequently, while less effective strategies are gradually minimized. This approach tailors treatment to each patient's individual response while increasing trial efficiency by concentrating resources on the most effective methodologies. By adopting these innovative trial designs, researchers can move closer to identifying the optimal tDCS parameters for depression.
Identifying patients
A promising strategy to enhance tDCS effectiveness is identifying patients who are most likely to benefit from this intervention. tDCS could be a particularly valuable option for patients who prefer to avoid medications or those unable to tolerate pharmacological treatments due to side effects or contraindications. Additionally, it may hold greater promise for non-resistant patients, including individuals experiencing their first episode of depression. For these patients, the decision to initiate long-term medication use can be challenging. In such cases, tDCS, as a noninvasive, well-tolerated intervention, presents an appealing alternative to traditional pharmacotherapy.
A more effective way to identify depressive patients who are likely to respond to tDCS is through precision approaches that account for individual patient characteristics. For example, an ancillary study of ELECT-TDCS identified four symptom clusters in depression: insomnia, atypical symptoms, core depressive symptoms, and guilt/anxiety. The study found that patients with insomnia responded better to tDCS, while those with guilt/anxiety or core depressive symptoms benefited more from pharmacotherapy.95 Another ELECT-TDCS ancillary study applied machine learning algorithms to analyze baseline features and predict treatment response in patients.96 For pharmacotherapy, key predictors included body mass index, anxiety levels, and cognitive scores, whereas for tDCS, the strongest predictors were negative affect and the number of depressive episodes. Such findings suggest phenotypic factors could guide the personalization of treatment strategies (Figure 2C). However, these findings are limited by the lack of external validation and reliance on a single clinical trial.
In terms of biological markers, Nord et al.30 found patients with MDD and higher baseline neural engagement in the left PFC during a working memory task exhibited greater clinical responses to a sequential prefrontal tDCS and CBT intervention compared to those who received sham tDCS and CBT.
CONCLUSION
Over the past decade, tDCS studies have primarily focused on MDD patients who did not respond to first-line treatments, demonstrating a moderate effect size compared to placebo tDCS. Methodologically, studies have consistently used electrode placements over the DLPFC and applied an electric current of 2 mA. Notably, more recent trials have shown improvements in methodological quality, primarily due to the inclusion of larger sample sizes. However, high methodological variability remains across studies, underscoring the need for further research to refine its potential benefits and limitations. In this review, we proposed several strategies to reduce variability and ultimately enhance the efficacy of tDCS for MDD while furthering our understanding of its mechanisms of action. These include spatial and temporal optimization of tDCS parameters, as well as novel methodological strategies, such as home-based and accelerated protocols, innovative trial designs, and the identification of patient profiles. In conclusion, while tDCS holds significant promise as a treatment for MDD, its widespread adoption will depend on overcoming current limitations through the development of optimized and personalized treatment protocols in the future.
SUPPLEMENTARY MATERIALS
ACKNOWLEDGEMENTS
PHRS is supported by Fundação de Amparo à Pesquisa do Estado de São Paulo (FAPESP; grant 2022/03266-0). MAV receives funding from Research Foundation - Flanders (FWO) and Ghent University (grants G044222N, G044019N, BOF17/STA/030, 01G00623). ARB receives grants from Conselho Nacional de Desenvolvimento Científico e Tecnológico (CNPq; PQ-1B) and FAPESP (grants 2018/10861-7, 2019/06009-6). LBR is currently supported by FWO (grant 12AZO24N).
 PDF
 Print
 Send this article by email
 How to cite this article
 Submit a comment
 Mendeley
 Pocket
 Share on Facebook
 Share on Twitter



