



ABSTRACT:
OBJECTIVE: Post-traumatic stress disorder (PTSD) is triggered by traumatic events, but genetic
vulnerability and a history of childhood trauma may also increase the risk of PTSD
onset. Thus, we investigated the interaction between genetic susceptibility according
to polygenic risk score (PRS), and traumatic events.
METHODS: We evaluated 68 women with PTSD who had been sexually assaulted and 63 healthy controls
with no history of sexual assault. DNA was genotyped using the Infinium Global Screening
Array (Illumina, San Diego, CA, USA), and PRS analysis was performed using PRSice.
Logistic regression models were also used to determine the interaction between childhood
trauma, traumatic life events, and PRS and how they contribute to PTSD risk.
RESULTS: We found a significant association between PRS, childhood trauma (p = 0.03; OR = 1.241),
and PTSD. There was also an interaction between PRS, traumatic life events, and childhood
trauma, particularly physical and emotional neglect (p = 0.028; OR = 1.010). When
examining neglect separately, we found a modest association between emotional neglect
and PTSD (p = 0.014; OR = 1.086).
CONCLUSION: Our findings highlight the importance of considering genetic vulnerability and traumatic
experiences in understanding the etiology of PTSD.
Keywords: PTSD; sexual assault; polygenic risk score; genome-wide association study; childhood trauma.
FIGURES
| Received: August 02 2023; Accepted: February 11 2024 |
INTRODUCTION
Post-traumatic stress disorder (PTSD) is a clinical condition that can occur after traumatic experiences, such as sexual assault.1 In Brazil, the prevalence of PTSD in women who have suffered sexual assault is estimated at 45%.2 The etiology of PTSD is complex and depends on multiple genomic variants, environmental factors, and prior trauma.3 Previous studies have suggested that prior trauma, including adverse experiences in early childhood and adulthood, increases the risk of PTSD.4 However, it remains unclear how repeated stress from trauma affects brain development and subsequently contributes to the development and progression of PTSD.
Genetic studies, including heritability and genome-wide association studies (GWAS), have investigated the role of genetic variants in PTSD etiology. The heritability of PTSD is estimated at 26-35% in men5-7 and 72% in women.8 These findings suggest that an individual's genetic background and sex may contribute to observed biological variability in response to a traumatic event.9
GWAS have provided insight into the genetic architecture of PTSD. These studies have identified multiple genetic variants whose minor effects could contribute to PTSD onset,10,11 suggesting that a small proportion of phenotypic variance can be attributed to the additive genetic effects of single nucleotide variants (SNVs).
Increasing evidence indicates that polygenic risk scores (PRS) can help estimate genetic predisposition to PTSD by calculating an individual's genetic risk using GWAS data.12-14 However, most PTSD studies involving GWAS and PRS have been conducted on samples of male veterans of European ancestry. Moreover, these findings do not consistently replicate across diverse populations exposed to traumatic experiences.14,15
Considering the evidence suggesting that interactions between genetic variants and prior trauma are associated with PTSD, we hypothesized that childhood trauma and the occurrence of lifetime traumatic events, such as natural disasters, transportation accidents, fire, or explosions, may interact with an individual's genetic liability and increase the likelihood of PTSD onset. However, no studies have examined whether a combination of early trauma exposure, multiple traumas, and PRS increase susceptibility to PTSD. We aimed to identify potential SNVs, and biological pathways associated with PTSD and evaluate the predictive utility of PRS for PTSD. We examined whether traumatic events, including childhood trauma and traumatic life events in adulthood, interact with PRS, thus increasing susceptibility to PTSD. We used a gene-environment approach to explore the interplay between PRS and traumatic experiences, aiming to gain a better understanding of their collective influence on PTSD diagnosis.
METHODS
Study population
We evaluated 68 women who had been sexually assaulted and subsequently developed PTSD (PTSD group) and 63 healthy controls (HC group) from a Brazilian population. The PTSD group comprised civilians aged 18-45 years who had experienced sexual assault in the 6 months prior to inclusion. They were recruited from the Hospital Pérola Byington, a specialized center for women's health in São Paulo, SP, Brazil. The HC group comprised age-matched women with no history of sexual abuse or a psychiatric diagnosis. Participants were voluntarily recruited from the community through advertisements and social media platforms.
During the recruitment process, participants were excluded from the study if they met any of the following criteria: 1) diagnosis of a sexually transmitted disease; 2) diagnosis of schizophrenia or bipolar disorder; 3) any uncontrolled clinical disease; or 4) pregnancy. Additional information on this cohort can be found in Coimbra et al.16
Assessments
The Mini International Neuropsychiatric Interview was used in the PTSD and HC groups to identify psychiatric disorders according to DSM-IV criteria. The Childhood Trauma Questionnaire (CTQ) was used to investigate the history of childhood trauma and assess the five domains of early-stage traumatic experiences in both groups: emotional, physical, and sexual abuse and emotional and physical neglect.17,18
The Life Events Checklist (LEC) is a self-report measure used to assess the number of traumatic events that occur during an individual's lifetime. The LEC identifies traumatic events linked to PTSD onset, including "sexual assault," "fire or explosion," "any other very stressful experience," "natural disaster," "sudden unexpected death of someone close to you," etc.19
Education level was classified into two groups according to the number of completed years of schooling: 4-12 years and > 12 years.
Genotyping and quality control
Blood samples were collected from all participants (n=131) in ethylenediaminetetraacetic acid tubes (BD, Franklin Lakes, NJ, USA), and DNA was isolated using the Gentra Puregene Blood Kit (Qiagen, Hilden, Germany) according to manufacturer instructions. The Infinium Global Screening Array-24 1.0 BeadChip (Illumina, San Diego, CA, USA), which includes approximately 640,000 markers, was used for genome-wide genotyping.
We used PLINK 1.9 to conduct quality control procedures and perform the GWAS analysis.20 SNVs were excluded if the minor allele frequency was low (< 1%), the Hardy-Weinberg equilibrium was violated (p < 0.00001), or the missing genotype rate was high (> 10%). Individuals with a high heterozygosity rate (> three SD) or a high identity-by-descent score (PIHAT > 0.2) were removed.21 Through the quality control procedures, 155,223 SNVs were removed, 2,494 with a high missing genotype rate, 152,115 with a minor allele frequency < 1%, and 614 violated the Hardy-Weinberg equilibrium. A total of 15,047 variants classified as indels were excluded, leaving 468,688 SNVs for subsequent analysis.
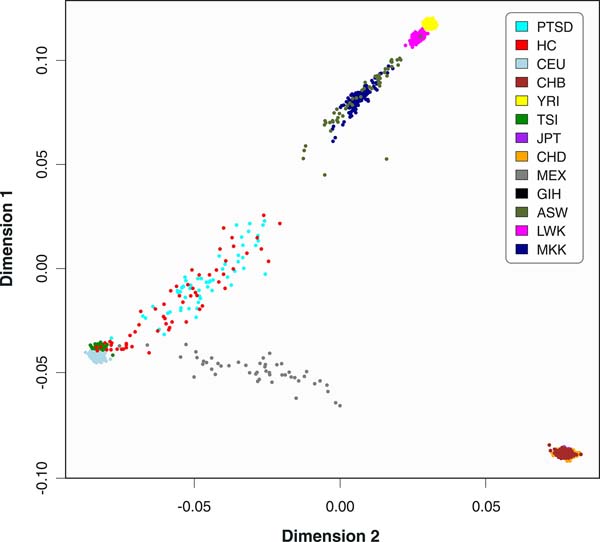
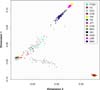
The 1000 Genomes Project Phase 3 was used as the reference population for principal component analysis (PCA) to address the significant genetic admixture of Brazil's population and ensure the reliability of the PRS data. To mitigate the impact of ancestry, 14 outliers (11 in the PTSD group and three in the HC group) were excluded based on discrepancies in the distribution plot of the principal component analysis. Subsequent analyses were conducted using a dataset of 117 participants, with 57 and 60 individuals in the PTSD and HC groups, respectively.
Genome-wide association studies and functional annotation
PLINK 1.9 was used to conduct the GWAS for PTSD, employing a logistic regression model and including the first 10 principal component (PCs) from PCA as covariates.21 Manhattan and quantile-quantile plots were generated using the "qqman" R package. We performed functional mapping and annotation of genetic associations to prioritize genes that offered insight into the genetic mechanisms underlying PTSD. Specifically, we focused on the top 100 SNVs (p < 0.0005786) from the GWAS using the default settings of the SNP2GENE function.22 A threshold of p < 5 × 10⁻⁸ was set for GWAS significance, and SNVs with p < 5 × 10⁻⁵ were considered suggestive of an association.
Polygenic risk score
PRSice 2.0 was used to calculate the PRS.23 These scores were derived by adding the weighted risk alleles and considering the effect size of each allele to generate individual risk scores for PTSD susceptibility. The PRS was generated using the PGC-PTSD Freeze 2 dataset,14 which represents the most extensively available GWAS of PTSD. This dataset comprises over 72,000 samples, with nearly 20,000 cases and 52,000 controls. PRS were adjusted for the first 10 genetic PCs to minimize the influence of potential confounding factors related to population stratification. In addition, the PRS was calculated at multiple p-value thresholds: 0.0001, 0.01, 0.05, 0.1, 0.5, and 1. The raw scores from the best p-threshold were transformed into z scores using PRSice 2.0.23 These standardized values were then employed in logistic regression models to predict PTSD diagnoses.
Statistical analysis
We conducted the statistical analysis in Jamovi 2.3.18 and generated graphs in R 4.3.1. We investigated the effects of age, per capita income, traumatic life events, total childhood trauma, and childhood trauma domains (emotional, physical, and sexual abuse and emotional and physical neglect) in the groups using non-parametric Mann-Whitney U tests. Differences in self-reported race and education level between the PTSD and HC groups were assessed using chi-square tests. Given the mixed ancestry of our sample, we examined the potential correlation between the PRS and PC using Spearman's correlation.
We used logistic regression models to test the association of PRS, childhood trauma, and/or traumatic life event interactions on PTSD. The first model used the diagnosis as an outcome, with standardized PRS, childhood trauma, and the interaction between PRS and childhood trauma as independent variables. Age, per capita income, education level, and the first 10 PCs were included as covariates in the analysis (PTSD diagnosis ~ PRS + CTQ + PRS × CTQ + age + per capita income + education level + PC1-PC10).
In the second model, instead of childhood trauma, we examined the interaction between individual domains of childhood trauma and PRS (PTSD diagnosis ~ PRS + CTQ domains + PRS × CTQ domains + age + per capita income + education level + PC1-PC10). Finally, we tested the simultaneous interaction of PRS, traumatic life events, childhood trauma, and its domains as contributing factors to PTSD diagnosis (PTSD diagnosis ~ PRS + LEC + CTQ + PRS × LEC × CTQ + age + per capita income + education level + PC1-PC10). Statistical significance was set at p < 0.05, and all regression models were adjusted using the Bonferroni correction for multiple comparisons based on the number of trauma scales tested (n = 7: LEC, total CTQ, and five CTQ domains).
Ethics statement
All participants provided informed consent before participating in the study, and the ethics committee of the Universidade Federal de São Paulo (CAAEs: 30332214.8.0000.5505, 30332214.8.0000.5505) approved the study protocol.
RESULTS
Descriptive analysis
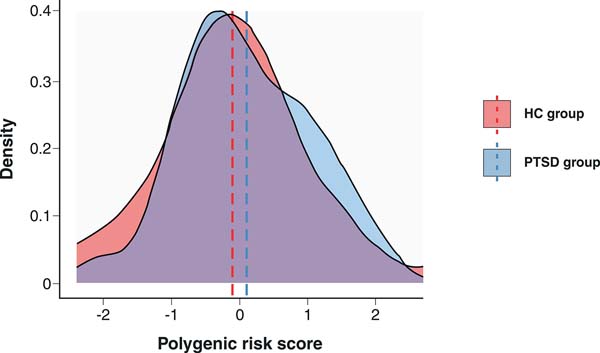
Table 1 presents the descriptive characteristics of 57 patients with PTSD and 60 HC. The mean age of the PTSD group was significantly lower than the HC group (p = 0.002). Per capita income (p = 0.013) and education level (p < 0.001) were significantly lower in the PTSD group than the HC group. We also identified a significant difference in racial classification, with the PTSD group consisting mainly of mixed race individuals (p = 0.013). Further, the means for childhood trauma (p = 0.009), emotional abuse (p = 0.010), physical abuse (p = 0.012), sexual abuse (p = 0.003), and traumatic life events (p < 0.001) were significantly higher in the PTSD group than the HC group. Finally, there was no significant difference in the mean standardized PRS between groups (p = 0.312) (Supplementary Figure S1). The PRS distribution curves for both groups are shown in Figure 1.
| Variable | PTSD group (n=57) | HC group (n=60) | p | Statistical test |
|---|---|---|---|---|
| Age (years) | ||||
| Mean (SD) | 24.60 (6.86) | 28.30 (7.50) | 0.002 | Mann-Whitney |
| Median (min-max) | 22 (18-44) | 26 (18-43) | ||
| Per capita income (BRL┼) | ||||
| Mean (SD) | 912 (1,213) | 1,835 (2,667) | 0.013 | Mann-Whitney |
| Median (min-max) | 600 (0-6,500) | 1,000 (0-15,000) | ||
| Education level (years), n (%) | ||||
| 4-12 | 32 (56) | 6 (10) | < 0.001 | Chi-square |
| > 12 | 25 (44) | 54 (90) | ||
| Race,╬ n (%) | ||||
| White | 26 (46) | 43 (71) | 0.013 | Chi-square |
| Black | 4 (7) | 4 (7) | ||
| Mixed | 27 (47) | 13 (22) | ||
| Childhood trauma | ||||
| Mean (SD) | 39.60 (14.40) | 32.60 (6.60) | 0.009 | Mann-Whitney |
| Median (min-max) | 34 (25-96) | 31 (25-55) | ||
| Childhood trauma domains | ||||
| Emotional abuse | ||||
| Mean (SD) | 9.70 (4.32) | 7.57 (2.93) | 0.010 | Mann-Whitney |
| Median (min-max) | 8 (5-21) | 6 (5-19) | ||
| Physical abuse | ||||
| Mean (SD) | 7.11 (3.61) | 5.64 (1.08) | 0.012 | Mann-Whitney |
| Median (min-max) | 6 (5-20) | 5 (5-10) | ||
| Sexual abuse | ||||
| Mean (SD) | 6.60 (3.90) | 5.08 (0.267) | 0.003 | Mann-Whitney |
| Median (min-max) | 5 (5-25) | 5 (5-6) | ||
| Emotional neglect | ||||
| Mean (SD) | 9.60 (4.63) | 8.49 (3.06) | 0.584 | Mann-Whitney |
| Median (min-max) | 8 (5-21) | 8 (5-20) | ||
| Physical neglect | ||||
| Mean (SD) | 6.58 (2.29) | 5.87 (1.30) | 0.060 | Mann-Whitney |
| Median (min-max) | 6 (5-18) | 5 (5-10) | ||
| Traumatic life events | ||||
| Mean (SD) | 5.07 (2.51) | 3.42 (2.25) | < 0.001 | Mann-Whitney |
| Median (min-max) | 4 (1-11) | 3 (0-11) | ||
| PRS | ||||
| Mean (SD) | 0.11 (0.95) | -0.07 (1.03) | 0.312 | Independent t-test |
| Median (min-max) | 0.01 (-2.13 to 2.08) | -0.09 (-2.40 to -2.67) |

The individuals were categorized into two groups based on their PTSD-PRS values: low risk and high risk. The top 25% of individuals with the highest PTSD-PRS values were classified as high risk. In contrast, the bottom 75% were classified as low risk. The childhood trauma score varied from 5 (indicating no maltreatment) to 25 (indicating severe maltreatment) for each domain. The statistical analysis showed that the PRS and all childhood trauma variables had higher mean values in the high risk group than the low risk group. Physical neglect, physical abuse, and childhood trauma (CTQ) were statistically significant with higher means in the high risk group than the low risk group. However, as the sample size was reduced to consider only the extremes (Q1-25% and Q4-75%), the statistical power was lower (Supplementary Tables S1 and S2).
Quality control analysis
Our sample had a diverse genetic ancestry: the HC group closer to European ancestry, while the PTSD group exhibited clustering towards African ancestry (Figure 2). Supplementary Figure S2 illustrates the distribution of the first three PCs used to genotype the sample.
Genome-wide association study and gene set enrichment analysis
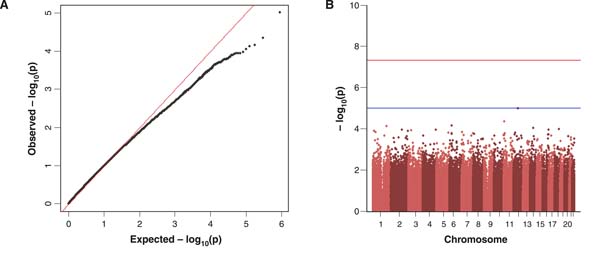
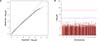
We performed a GWAS to search for potential SNV associated with PTSD, but none reached statistical significance (p < 5 ×10⁻⁸) between the case and control groups. However, we found a SNV that showed a suggestive association (p < 5×10⁻⁵) with PTSD: rs10878292 on chromosome 12 (p = 9.931 × 10⁻⁶, odds ratio [OR] for the G allele = 0.131). A quantile-quantile plot revealed a genomic inflation factor of 1.04 (Figure 3A). The Manhattan plot shows the p-values for each SNV in both groups (Figure 3B). According to functional mapping and annotation analysis of the top 100 SNVs from the GWAS, no pathways were significantly associated with PTSD (p > 0.05) (Supplementary Figure S3 showed the top 20 SNV). Supplementary Table S3 provides the main GWAS results.
Polygenic risk score findings
The most robust PRS predictions, obtained at the best p-value threshold of 0.333 (Nagelkerke's pseudo R2 = 0.087, p = 0.009), were used to investigate the association between predicted polygenic risk and the PTSD outcome and included 53,705 SNVs (Supplementary Figure S4). We found a non-significantly (p = 0.312) higher mean PRS in the PTSD group than the HC group (Figure S1). However, when we tested whether a history of trauma, genetic ancestry, age, education level, and per capita income influenced PTSD diagnosis via PRS effects, we found a significant association (adjusted p = 0.007; OR = 0.035) (Supplementary Table S4).
We also observed a negative correlation between PRS and the first PC (Rho = -0.734; p < 0.01). However, there were no significant correlations between PRS and the other PC (PC2-PC10). Figure S5 presents the Spearman correlations between PRS and the first 10 PCs.
We used PRS data to test whether the genetic factors measured in the PRS analysis interacted with traumatic events and predicted PTSD diagnosis (Table 2). We found an interaction between PRS and childhood trauma that was associated with an increased risk of PTSD, although it had a small effect size (adjusted p = 0.030; OR = 1.241). We also found that PRS interacted with childhood trauma domains (emotional, physical, and sexual abuse; emotional and physical neglect), slightly increasing the risk of PTSD in comparison with the HC group (adjusted p = 0.036; OR = 1.001). Furthermore, we investigated the interactions between childhood trauma, traumatic life events, and PRS, finding a suggestive association with PTSD (adjusted p = 0.049; OR = 1.015). Specific analysis revealed a significant interaction between PRS, traumatic life events, and childhood neglect (adjusted p = 0.028; OR = 1.010). However, when we examined neglect individually, only emotional neglect was significantly associated (adjusted p = 0.014; OR = 1.086) with PTSD risk. We found no evidence that PRS interacted separately with traumatic life events, i.e., PRS × LEC (adjusted p = 0.105). We also found no associations between PRS × LEC × physical abuse (adjusted p = 0.07), PRS × LEC × emotional abuse (adjusted p = 0.063), PRS × LEC × sexual abuse (adjusted p = 0.336), or PRS × LEC × physical neglect (adjusted p = 0.063).
| Predictors | Adjusted p | OR | 95%CI |
|---|---|---|---|
| PRS × Total CTQ | 0.030 | 1.241 | 1.066-1.445 |
| PRS × abuse┼ × neglect╬ | 0.036 | 1.001 | 1.000-1.001 |
| PRS × Total CTQ × LEC | 0.049 | 1.015 | 1.004-1.027 |
| PRS × LEC × neglect | 0.028 | 1.010 | 1.003-1.018 |
| PRS × LEC × emotional neglect | 0.014 | 1.086 | 1.030-1.145 |
All models were adjusted for the first 10 principal components, age, per capita income, and education level. The dependent variable was the diagnosis, which included post-traumatic stress disorder and healthy control groups.
× = interactions between predictors; CTQ = Childhood Trauma Questionnaire; LEC = Life Event Checklist (corresponding to traumatic life events); OR = odds ratio; PRS = polygenic risk score.
┼ Abuse = sexual, physical, and emotional domains.
╬ Neglect = physical and emotional domains.

DISCUSSION
Our study investigated the interaction between genetic variants (SNVs or PRS), traumatic events, and the risk of developing PTSD in a cohort of civilian women. The main finding was that childhood neglect, specifically emotional neglect, influences PTSD risk in individuals with a higher PRS. In this context, our analysis confirmed a significantly predictive polygenic risk for PTSD, although it was not sufficient for clinical use. This is the first study to demonstrate that childhood traumatic events interact with PRS to influence PTSD risk.
We found limited evidence to support an association between PRS and PTSD, even after accounting for various risk factors, such as the first 10 PCs, education level, per capita income, age, childhood trauma, and life events. Surprisingly, the results indicated an inverse relationship, with cases having a lower PRS (Supplementary Table S2) than controls. However, this finding must be interpreted carefully, since PC1 may have captured PRS and diagnostic differences between the PTSD and HC groups rather than reflecting PRS alone. Furthermore, PC1 showed a robust negative correlation with PRS (Supplementary Figure S5), demonstrating that lower PRS was correlated with higher PC1. In addition, when examining the PRS differences between the PTSD and HC groups without adjusting for risk factors, we found no significant association between PRS and PTSD. Thus, we believe that the negative correlation between PRS and PTSD diagnosis can be attributed to sample selection bias, given that genetic ancestry differences between the PTSD and HC groups may have influenced the outcome.
The prediction efficiency of PRS in previous PTSD studies of samples with mixed ancestry has been inconsistent. Waszczuk et al.24 and Gelernter et al.25 found no association between PRS and PTSD onset in European victims of the World Trade Center disaster and in multi-ethnic participants of the Million Veteran Program, respectively. However, Weber et al.26 and Misganaw et al.27 found a significant association between PRS and PTSD onset in southeastern Europeans and in multi-ethnic veterans, respectively. This was inconsistently observed in our study, which aligns with the findings of Talarico et al.,28 who conducted a PRS analysis in a Brazilian population. They found that predicting outcomes for non-European and mixed-race populations is a more complex and challenging task.28
Some studies have found that early-life adversities lead to a higher risk of psychiatric disorders.29-31 Our results suggest that childhood trauma is an essential risk factor for PTSD. Childhood adversity can increase the risk of brain development alterations, particularly in the cognitive domain. These alterations can manifest as memory problems, learning difficulties, cognitive delays, emotional regulation difficulties, and attention and behavioral issues. These neurodevelopmental changes may increase the risk of psychiatric disorders, interpersonal problems, and antisocial activities.32 It is well known that childhood neglect can lead to various negative outcomes, including altered stress response and an increased risk of mental health disorders.33 The hypothalamic-pituitary-adrenal pathway is a key biological system that can be affected by childhood neglect. This pathway regulates the body's response to stress by releasing stress hormones, such as cortisol.34,35 It is possible that genetic factors may affect how an individual's hypothalamic-pituitary-adrenal axis responds to stressors like neglect, and individuals with a high PRS may have a different response to childhood neglect due to their genetic background. However, based on the results of our study, we cannot definitively state whether PRS predicts an individual's propensity for an exacerbated response to trauma mediated by the hypothalamic-pituitary-adrenal axis. In addition to brain alterations, genetic variants (SNVs) have also been linked to childhood trauma and PTSD, although the specific biological mechanisms underlying these associations remain unclear.36
Thus, this study examined the potential association between PRS, childhood trauma, and lifetime exposure to potentially traumatic events and PTSD onset. Traumatic events are prevalent in the general population, and epidemiological studies indicate that approximately 70% of individuals experience at least one traumatic event during their lifetime.37 Kessler et al.38 found that, on average, individuals who have suffered any lifetime trauma have experienced 2.9 types. High rates of PTSD are often associated with a high number of traumatic events.39 Our study supports these previous findings by demonstrating that the interaction between early life adversity, the number of trauma types, and genetic predisposition (as PRS) may enhance diagnostic assessment in vulnerable individuals.
Although no SNV were associated with PTSD, we found a suggestive association between rs10878292 and PTSD. No previous studies have found evidence of a clinically significant association between this SNV and PTSD risk. Our gene set enrichment analysis suggested that the ITPR2 and HLA-B genes were significantly associated with biological pathways related to PTSD. ITPR2 (inositol 1,4,5-trisphosphate receptor type 2) is involved in glutamate-mediated neurotransmission and plays a crucial role in cell apoptosis. It has been associated with bipolar disorder and has been shown to cause abnormalities in the brains of mice with depressive-like behavior.40 Patients with PTSD have extensive immune dysregulation, and it is well-established that HLA-B (major histocompatibility complex, class I, B) plays a central role in the immune system. Allelic variations in HLA-B are associated with an increased risk of PTSD and other major psychiatric disorders.41
Our findings should be interpreted in the context of several limitations. First, the study population's racial diversity may have introduced a confounding factor, although we accounted for the first 10 PCs of our logistic models to mitigate this diversity. However, caution should be exercised when generalizing these results to other populations. There are also potential comorbidities we did not include in our analyses that may be associated with PTSD, such as depression, anxiety, mood disorders, and substance use. Second, childhood trauma and traumatic life events were assessed with self-report measures, which could be subject to response bias. Respondents may have been reluctant to answer truthfully, particularly when confronted with sensitive questions. It should also be considered that the respondents may not have evaluated themselves accurately. Third, it is important to acknowledge that unmeasured confounders may have influenced the outcome of interest, despite our adjusting all models for known potential biases.
Furthermore, it is worth noting that the power of PRS association studies is typically optimized when large sample sizes are used for both the base and target samples. While our sample size for the GWAS was smaller than other studies, it is important to mention that the developers of PRSice recommend a minimum of 100 individuals in the target data. No specific instructions regarding the base data sample size were found in over 72,000 samples. The main strength of this study is its population. We focused on civilian women who had experienced sexual assault 1 to 6 months prior to study inclusion. This focus on a specific population allowed us to examine gene-trauma interactions in a mixed and vulnerable population during the early stages of PTSD.
In conclusion, this study expands on previous research by investigating the association between PRS and PTSD. We also explored the interactions between PRS and PTSD, childhood trauma, and other traumatic experiences. Our findings showed the importance of the emotional neglect domain combined with other lifetime traumatic events and an individual's genetic background (measured by PRS) in increased PTSD risk.
This study highlights the importance of integrating a gene-environment approach into psychiatry. Future research should explore these associations using specific diagnostic and genetic measures.
ACKNOWLEDGEMENTS
The authors would like to thank the participants and staff who collaborated in all stages of this cohort study. This study was supported by Fundação de Amparo à Pesquisa do Estado de São Paulo (FAPESP; grant 2014/12559-5 and grant 2015/26473-8), Coordenação de Aperfeiçoamento de Pessoal de Nível Superior (CAPES, Finance Code 001), Conselho Nacional de Desenvolvimento Científico e Tecnológico (CNPq; grant 312402/2021-0), Programa de Atendimento a Vítimas de Violência e Estresse (PROVE), and Departamento de Psiquiatria, Universidade Federal de São Paulo (UNIFESP).
 PDF
 Print
 Send this article by email
 How to cite this article
 Submit a comment
 Mendeley
 Pocket
 Share on Facebook
 Share on Twitter



